
Prostate Cancer

What is Prostate Cancer?

Prostate cancer consists of an abnormal and uncontrolled proliferation of cells in the prostate gland—a structure of the male reproductive system responsible for producing part of the seminal fluid. By multiplying abnormally, these cells acquire the ability to invade adjacent tissues and, in more advanced stages, spread to other organs (a process known as metastasis).

This is a pathology markedly associated with aging. Although the average age at diagnosis is around 65 years, the risk begins to rise significantly from ages 45-50.

Incidence and Risk Factors

Prostate cancer is the most frequent malignant tumor in men in the Western world, representing the second leading cause of cancer death in males. In Portugal, statistics point to the diagnosis of about 6,000 new cases annually, with the disease being responsible for approximately 1,700 to 1,800 deaths per year.
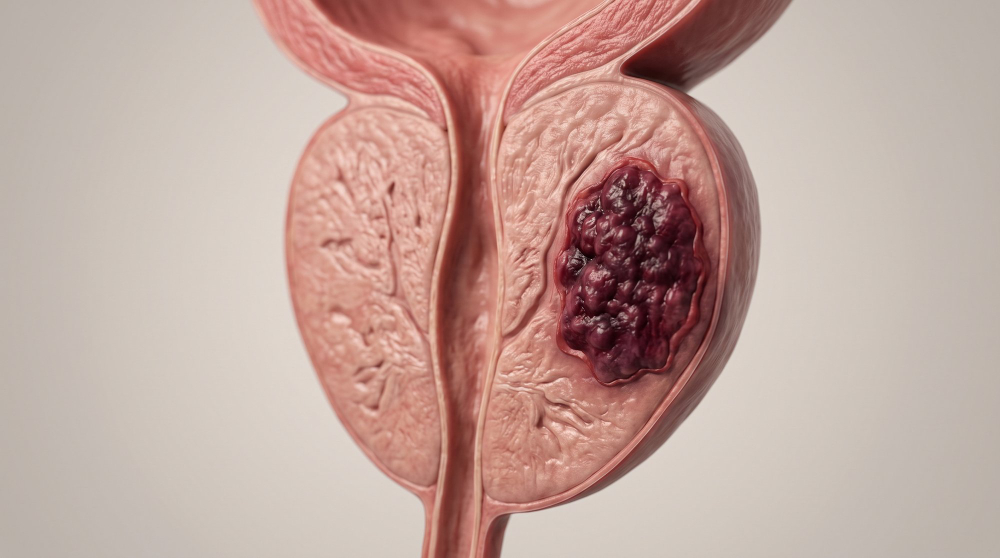
The development of this neoplasm depends on a complex interaction between genetic and environmental factors. The main established risk factors are:

  • Age: The risk increases progressively with advancing years.
  • Family History and Genetics: Men with first-degree relatives (father or brothers) with a history of prostate or breast cancer present a substantially higher risk. Mutations in the BRCA1 and BRCA2 genes are directly associated with more aggressive forms of the disease.
  • Ethnic Origin: There is a higher incidence and aggressiveness in men of African-American descent.
Symptoms of Prostate Cancer

In its initial phase—when the tumor is strictly localized and confined to the prostate—prostate cancer is usually asymptomatic. This means that the patient may feel perfectly well, without any change in their urinary routine, and still have a developing tumor.

When the disease progresses or reaches a locally advanced or metastatic state, clear clinical manifestations may appear, such as a weak, interrupted, or hesitant urinary stream; a marked increase in urinary frequency (especially at night);

  • Weak urinary stream, increased frequency, or urinary urgency
  • Sensation of incomplete bladder emptying;
  • Presence of blood in the urine (hematuria) or in the semen;
  • Urinary incontinence or, in rarer cases, fecal incontinence;
  • Persistent bone pain (a frequent sign of spread to the skeleton);
  • Loss of strength or sensitivity in the legs.

Although urinary symptoms are very common with age, often being associated with Benign Prostatic Hyperplasia (BPH), evaluation by a urologist is recommended to unequivocally exclude the presence of malignancy.

Diagnosis of Prostate Cancer

Early Diagnosis and Screening

Given the silent nature of the disease in the initial phase, early diagnosis is the most effective tool to ensure a cure. It consists of regular periodic evaluation (usually annual) from ages 45-50 through two simple complementary exams:

  1. PSA Test (Prostate-Specific Antigen): A blood test that measures the levels of this protein produced by the prostate. High values or those that rise rapidly over time constitute a warning sign.
  2. Digital Rectal Examination: A quick and painless clinical observation that allows the urologist to palpate the surface of the prostate, evaluating its size, consistency, and the possible presence of suspicious nodules.

Confirmatory Exams

Faced with a change in PSA or the digital rectal exam, the urologist outlines an individualized investigation strategy, which may include:

  • Multiparametric Magnetic Resonance Imaging of the Prostate (mpMRI): An advanced imaging exam that maps the prostate with high precision, identifying suspicious areas and guiding the next steps.
  • Prostate Biopsy (or Fusion Biopsy): The only definitive method to confirm the diagnosis. It consists of collecting small fragments of prostate tissue under ultrasound guidance. In a fusion biopsy, images from the previous MRI are overlaid in real-time with the ultrasound, allowing the needle to be directed exactly at the suspicious target, drastically increasing the precision of the exam.

Staging and Follow-up

If the presence of cancer is confirmed, it becomes necessary to determine the extent of the disease through staging exams such as Computed Tomography (CT), Full Body Bone Scintigraphy or, increasingly, PSMA-PET—a state-of-the-art Nuclear Medicine exam with superior sensitivity for detecting microscopic tumor foci.

Treatments and Surgeries for Prostate Cancer

The therapeutic approach to prostate cancer is not universal; it must be strictly individualized based on the tumor’s degree of aggressiveness (ISUP or Gleason Score), the staging, the chronological and biological age of the patient, their comorbidities, and their personal preferences.

The main curative and advanced therapeutic options available are detailed below:

1. Radical Prostatectomy (Surgery)

Consists of the complete surgical removal of the prostate gland and seminal vesicles. It is one of the standard treatments of excellence for localized cancer.

  • Surgical Approaches: It can be performed via open surgery (classic incision below the navel), conventional laparoscopic surgery (through small holes in the skin and directly manipulated instruments), or robotic laparoscopic surgery (where the instruments are operated by the urologist through a high-precision robotic console).
  • Advantages: It presents excellent long-term oncological cure rates (about 95% of patients with localized tumors are disease-free at 5 years); it allows for the total anatomopathological analysis of the surgical specimen for an exact prognosis; and it preserves the possibility of salvage treatments (such as radiotherapy) if the disease returns.
  • Recovery and Side Effects: The average hospital stay varies between 2 to 4 days and the patient needs to maintain a urinary catheter for 7 to 14 days. In the first few weeks, it is normal to have some urine leakage, which tends to recover progressively—after one year, 90-95% of patients present complete urinary continence. The impact on erectile function depends on whether the cavernous nerves are preserved and the patient’s previous state; however, through modern pelvic and pharmacological rehabilitation programs, more than 50% of patients maintain an active sexual life after one year.

2. Robotic Stereotactic Radiotherapy (Cyberknife)

Cyberknife is a cutting-edge technology in the field of External Radiotherapy (SBRT/Radiosurgery). It uses an ultra-precise robotic arm that tracks the body’s respiratory and physiological movements in real-time.

  • Indication: Indicated for localized low or intermediate-risk prostate cancer.
  • Advantages: A completely non-invasive technique, performed on an outpatient basis (does not require hospitalization), without the need for catheterization or anesthesia. While conventional radiotherapy requires daily treatments for 4 to 6 weeks, Cyberknife reduces the protocol to just 5 sessions concentrated in a single week. It maximizes the radiation dose to the tumor while preserving adjacent healthy tissues (bladder and rectum), substantially reducing the risks of impotence, urinary incontinence, radiation cystitis, or proctitis.
  • Preparation: Before treatment, small titanium markers are implanted in the prostate and a hydrogel spacer can be applied between the prostate and the rectum, which temporarily moves the organs apart to mitigate the effects of radiation on the intestine.

3. Prostate Brachytherapy (Internal Radiotherapy)

This approach consists of the direct introduction of tiny radioactive implants (“seeds”) into the prostate tissue through the perineum, guided by a computerized system under anesthesia.

  • Indication: Localized low or intermediate-risk cancer, preferably in patients with normal prostate volume (<50-60 cc) and good previous urinary function.
  • Advantages: A minimally invasive procedure that requires a very short hospital stay (<24 hours). The catheter is removed just a few hours after the procedure. The seeds emit localized radiation over a few months, later becoming inert and permanent. It offers a very low risk of incontinence or erectile dysfunction.
  • Considerations: It may cause some transient irritative urinary symptoms (burning, urgency, weak stream) in the first year, effectively managed with medication.

4. Other Therapeutic Approaches

  • Active Surveillance: For very low-aggressiveness tumors, the choice is often not to treat immediately, monitoring the patient closely (PSA, mpMRI, and serial biopsies) to intervene only if there are signs of progression, avoiding overtreatment.
  • Treatment of Advanced or Metastatic Disease: In scenarios where the tumor has spread beyond the limits of the prostate, Androgen Deprivation Therapy (Hormone Therapy) is used to block testosterone (the tumor’s “fuel”). Currently, these drugs are combined with second-generation hormone therapies (such as apalutamide, abiraterone, enzalutamide), chemotherapy (docetaxel/cabazitaxel), or radiopharmaceuticals (Radium 223), ensuring prolonged disease control and preservation of quality of life.
Do you have an elevated PSA? You should repeat the test a few weeks later, but if it remains high, you must rule out the presence of prostate cancer. Schedule an urgent evaluation appointment.

Appointment booking

Book your urology appointment with Dr Frederico Furriel, a urologist with consultations in Leiria, Caldas da Rainha and Porto de Mós. Select your preferred location and submit your appointment request.